
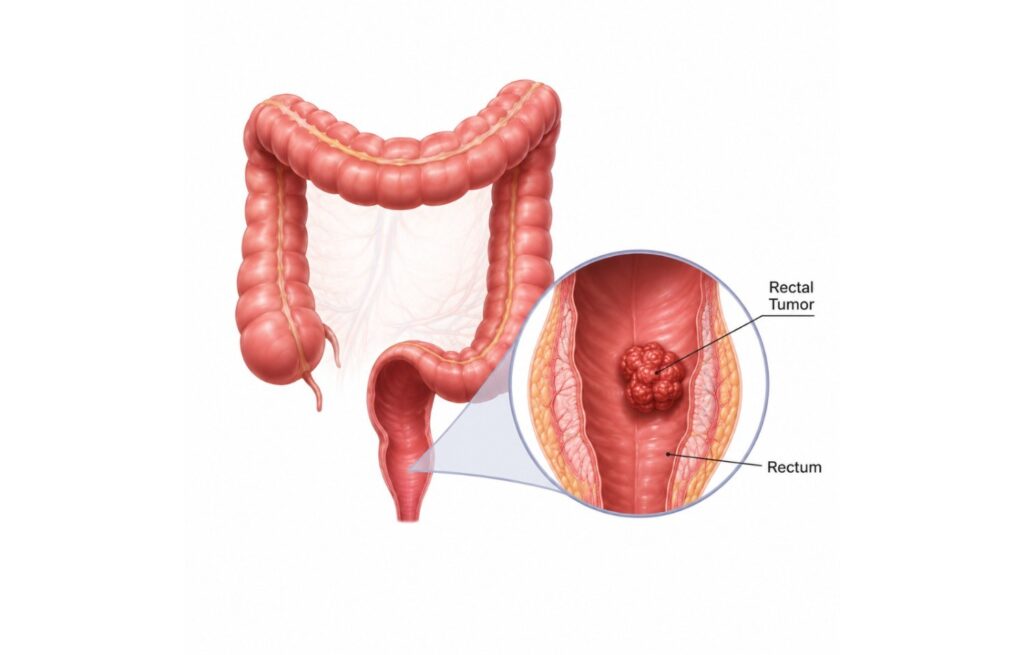
Hearing the words “rectal cancer” is frightening enough on its own. Then comes a wave of decisions — which treatment, which surgeon, which hospital — often within days of a diagnosis that still hasn’t fully sunk in. At Zanish Cancer Hospital in Naranpura, Ahmedabad, Dr. Nishanth Sanghavi and his surgical oncology team offer robotic and minimally invasive surgery for rectal cancer, with the goal of removing the tumor completely while protecting the function and quality of life that matter most to you — including, wherever medically possible, avoiding a permanent stoma.
This page explains what robotic rectal cancer surgery actually involves, who it’s suitable for, and what to expect before, during and after the procedure.
Robotic rectal cancer surgery is a minimally invasive technique in which the surgeon operates through a few small incisions using a robotic-assisted surgical system, rather than the large single incision used in open surgery. The surgeon is in control at all times — the robotic arms translate the surgeon’s hand movements into smaller, steadier motions inside the pelvis, guided by a magnified, high-definition 3D view of the surgical field.
The rectum sits deep within a narrow, bony pelvis, close to nerves controlling bladder and sexual function. This is precisely why robotic precision matters here more than in many other abdominal cancers: the confined space makes fine, stable movement and a clear 3D view genuinely useful for the surgeon, not just a marketing point.
The core surgical goal — regardless of technique — is a total mesorectal excision (TME): removing the rectal tumor along with the surrounding fatty tissue (mesorectum) and lymph nodes as one intact unit. This remains the internationally recognized standard for rectal cancer surgery, and robotic assistance is used to help perform it with precision in a tight anatomical space.
Suitability depends on several factors that Dr. Sanghavi and the multidisciplinary team assess together, including:
Not every patient is a candidate for a robotic approach, and that’s a normal, expected part of surgical planning — not a shortcoming of the patient. Your case will be reviewed on its own merits, typically at a multidisciplinary tumor board involving surgical oncology, medical oncology, and radiation oncology.
Depending on where the tumor sits and how advanced it is, the operation performed is usually one of the following:
Wherever it is oncologically safe to do so, the surgical plan is built around preserving normal bowel function — but tumor clearance always takes priority over preservation. This is discussed openly during consultation, because it’s usually the question patients care about most.
Zanish Cancer Hospital performs robotic rectal cancer surgery using an advanced robotic-assisted surgical platform. A few clarifications patients often ask about:
Compared with traditional open rectal cancer surgery, robotic and other minimally invasive approaches are generally associated with:
These are general patterns seen across minimally invasive surgery, not guarantees for every individual case. Your recovery will depend on tumor stage, any prior treatment, overall health, and how your body responds — something your surgical team will discuss honestly with you, without overpromising an outcome.
Dr. Nishanth Sanghavi is a surgical oncologist and the Director & Consultant Surgical Oncologist at Zanish Cancer Hospital, a role he has held since March 2018. His training includes an M.S. in General Surgery from Smt. NHL Municipal Medical College, Shardaben Hospital, Ahmedabad, and an M.Ch. in Surgical Oncology from the Gujarat Cancer and Research Institute (GCRI), Civil Hospital, Ahmedabad — one of India’s leading government cancer centres. He also trained in advanced laparoscopic oncosurgery under Dr. Shailesh Putambekar at Galaxy Care Institute, Pune.
With over 14 years of experience and more than 5,000 cancer surgeries performed, his practice spans GI oncology (including colorectal and rectal cancer), uro-oncology, gynecologic oncology, head & neck oncology, and breast cancer surgery. He has also participated in national oncology forums, including as Conference Director and Chairperson at events such as the Thoracic and Colorectal Oncology Summit (TACOS).

MBBS - 2006

M.S. in General Surgery - 2010
M.Ch. in Surgical Oncology - 2014
Advanced laparoscopic oncosurgery
Before surgery: Your case is reviewed with imaging (MRI/CT), colonoscopy and biopsy findings, and staged appropriately. Locally advanced tumors are often treated with chemoradiation first, followed by a rest period before surgery to allow the tumor to respond.
During surgery: The operation is performed under general anaesthesia. Depending on complexity, robotic rectal cancer surgery typically takes several hours. Your surgical team will give you a case-specific estimate.
In hospital afterward: Most patients are mobilised within a day of surgery to support recovery and reduce complications. Hospital stay length depends on the procedure performed and how your recovery progresses — your team will give you a realistic, individualized timeline rather than a generic number.
At home: Diet is reintroduced gradually, and activity is increased in stages. If a temporary ileostomy was created, stoma care guidance and support are provided, along with a plan and approximate timeline for reversal surgery.
As with any major surgery, robotic rectal cancer surgery carries risks, which may include bleeding, infection, anastomotic leak (a leak at the reconnected bowel), changes in bowel or bladder function, and — in some cases — the need for a temporary or permanent stoma depending on tumor location. Robotic and minimally invasive techniques aim to reduce certain risks compared to open surgery, but they do not eliminate them. Your surgical team will walk you through the specific risks relevant to your case, your tumor stage, and your overall health, so you can make an informed decision.
The cost of robotic rectal removal surgery in Ahmedabad varies based on the specific procedure (LAR, APR, or ISR), whether a stoma or reversal is involved, length of hospital stay, and any pre- or post-operative treatment required. Insurance, including Medi-Claim, is accepted at Zanish Cancer Hospital. For an estimate specific to your diagnosis, book a consultation — general online cost figures for rectal cancer surgery are rarely accurate for an individual case.
If you’ve already received a treatment recommendation elsewhere, seeking a second opinion before surgery is a reasonable and common step — not a sign of distrust in your existing care team. Dr. Sanghavi and team review medical reports, biopsy results, and imaging to discuss whether robotic or minimally invasive rectal surgery may be appropriate for your specific case.
Rectal cancer treatment decisions move fast, but you deserve time to understand your options clearly before choosing one. If surgery has been recommended, or you’d like a second opinion, the team at Zanish Cancer Hospital is available to talk through your case honestly.
Lorem Ipsum is simply dummy text of the printing and typesetting industry. Lorem Ipsum has been the industry’s standard dummy text ever since.
It depends on the type of urinary diversion chosen. An ileal conduit uses an external bag; a neobladder allows many patients to urinate through the urethra without one; a continent cutaneous diversion uses a stoma the patient self-catheterizes rather than a continuous external bag. Your surgical team will help decide which is right for you before surgery.
Current research shows robotic radical cystectomy achieves comparable cancer control and survival outcomes to open surgery, while offering advantages like less blood loss and, in many cases, shorter hospital stays.
Recovery timelines vary, but most patients need several weeks to a couple of months to return to normal activity, depending on the type of urinary diversion and individual health.
For some patients with muscle-invasive bladder cancer, chemotherapy before surgery (neoadjuvant chemotherapy) is recommended to improve outcomes. Whether this applies to you depends on your specific diagnosis and stage.
Yes. Zanish Cancer Hospital in Ahmedabad offers robotic-assisted uro-oncology surgery, including for bladder cancer, under Dr. Nishant Sanghavi.
This decision depends on your kidney function, extent of disease, prior treatments, and personal preference regarding daily management. It’s best made in detailed conversation with your surgical team well before your operation date.

Lorem ipsum dolor sit amet consectetur. Tempus libero lectus id velit fermentum et tempus egestas lobortis.
Copyright © 2023 Wise Doctor By Evonicmedia All Rights Reserved.
Powered by Evonicsoft

Advancing Cancer Care Through Robotic Precision
Zanish Cancer Hospital is committed to providing advanced cancer care through modern robotic surgery, comprehensive treatment, and compassionate care for every patient.
This will close in 0 seconds